
رعاية الدماغ والجهاز العصبي
Progress in China: Brain-computer interfaces(IMIE) help retinitis pigmentosa patients regain their sight
محتويات الصفحة
The problem IMIE is trying to address
Retinitis pigmentosa, or RP, is a group of inherited retinal degenerations. In many forms of RP, rod photoreceptors are affected first, leading to night blindness and progressive loss of peripheral vision. Cone function may later decline as well. People with advanced disease can be left with a very narrow visual field or no useful light perception.
A retinal prosthesis does not repair the genes that caused RP, and
it does not regrow lost photoreceptors. Instead, it tries to use retinal
neurons that may remain downstream of the damaged photoreceptors. By
electrically stimulating those cells, the device aims to create small percepts
of light, known as phosphenes.
What the IMIE system contains
IMIE stands for Intelligent Micro Implant Eye. In the first published human study, the system used a 256-channel epiretinal implant. The electrode array was positioned on the inner surface of the retina near the macular region. An external camera, video processing hardware, wireless transmission components, and clinical fitting software completed the signal chain.
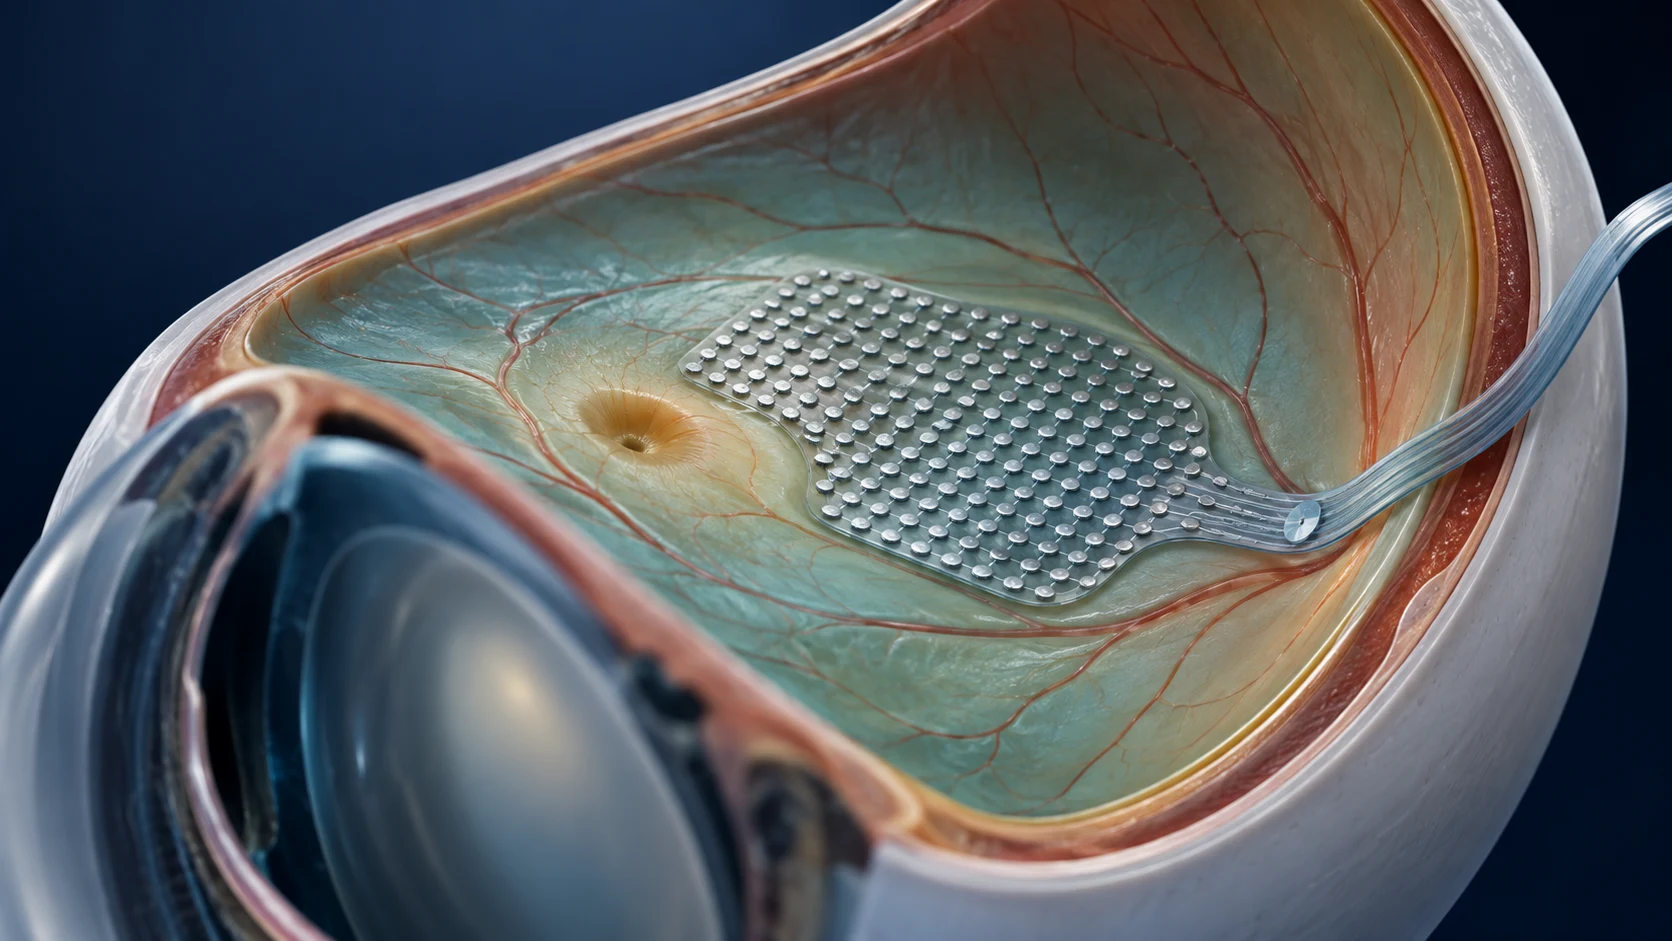
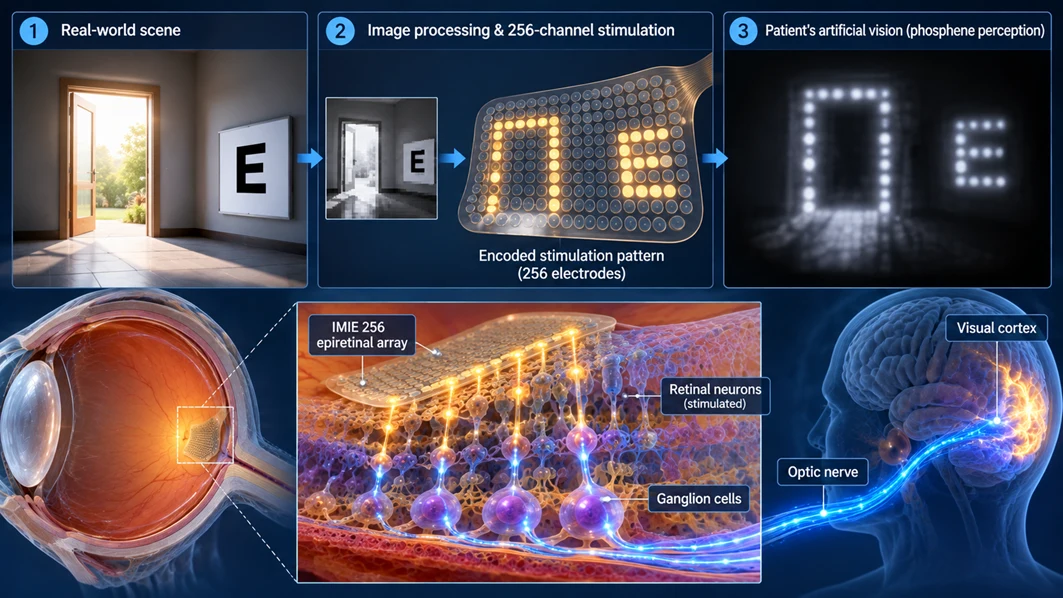
The camera captures a scene, but the wearer is not shown a conventional image. The processor extracts and simplifies high-contrast information, such as edges, lines, movement, or the outline of a doorway. That information is mapped to selected electrodes according to the participant's individually measured stimulation thresholds.

From electrical pulses to a visual percept
When an electrode delivers a controlled pulse, nearby retinal neurons may be activated. Signals then travel through the optic nerve and the rest of the visual pathway. The resulting percept is generally described as points or patterns of light rather than detailed, natural vision. A doorway may appear as a sparse outline; a moving object may be represented by a shifting cluster of light.
This distinction matters. A higher electrode count can offer more possible stimulation locations, but it does not translate directly into the pixel count of a normal display. Current spread, neural survival, electrode placement, perceptual interactions, and the brain's ability to interpret a new code all affect what the user can perceive.
What the first human study found
A 2021 peer-reviewed report described five people with end-stage RP who received the IMIE 256 implant in one eye. After surgery and fitting, participants completed 90 days of visual rehabilitation. With the system switched on, performance was generally better than with the system switched off or at baseline across grating, Tumbling E orientation, motion, square localization, line, and doorway tasks.
The study reported a best grating result equivalent to 20/800 and a best Tumbling E result equivalent to 20/1200. These measurements show that electrically elicited visual information could be used in structured tests. They should not be interpreted as restoration of ordinary reading vision, face recognition, color perception, or independent navigation in uncontrolled environments.
Rehabilitation is part of the technology
Users must learn a new sensorimotor routine. They may need to scan with their head, aim the camera, compare repeated phosphene patterns, and link those patterns to objects in the environment. The 90-day training period in the early study underscores that the functional result depends on both the hardware and sustained learning.
Risks and evidence limits
The first human report was small and had limited follow-up. The authors also disclosed relationships with companies involved in the technology. That does not invalidate the findings, but it is relevant when interpreting an early feasibility study. Larger cohorts, longer follow-up, independent replication, and evidence about daily-life benefit are still needed.
Where the field stands in 2026
In April 2026, the manufacturer announced the formal launch of a new clinical trial after ethics approval. This is evidence of continued clinical development, not evidence that the device has already become an established treatment. Manufacturer announcements should be read separately from peer-reviewed clinical outcomes.
The most accurate conclusion today is cautious but meaningful: IMIE offers a research path toward rebuilding basic artificial vision for some people with profound RP-related blindness. It is not a proven cure, it will not necessarily suit every patient, and eligibility or expected benefit can only be assessed by a specialist clinical team within an authorized study or approved care pathway.
References
Xu H, et al. First Human Results With the 256 Channel Intelligent Micro Implant Eye (IMIE 256). Translational Vision Science & Technology. 2021;10(10):14. doi:10.1167/tvst.10.10.14. PMID: 34705041; PMCID: PMC8556567.
Intelligent Micro Technology. IMIE clinical trial launch announcement. 2 April 2026. Manufacturer source; accessed 6 October 2026.
كيف ننسق
ملاحظة مهمة
تقدم هذه الصفحة معلومات عامة وتصف نطاق التنسيق؛ وهي ليست نصيحة طبية. يجب أن تشرح المستشفى المستقبلة الملاءمة والفائدة المتوقعة والمخاطر بعد التقييم الكامل.